

All images created by the author.
It’s a drizzly Friday in late autumn, the kind of evening where the streetlights have halos and the windshield keeps fogging at the edges no matter what you do with the defroster. You and your partner just wrapped your third call of the shift, a “lift assist” that turned into a full transport and took longer than expected. You’re talking about what to grab on the way back to the station. The conversation is firmly in the “we deserve tacos” camp when the CAD chirps.

You’re going to a 44-year-old female with shortness of breath and chest pain. The address is 1836 Conference Dr. at a hotel near the convention center. It says in the notes it started over the past several hours. Nothing about the dispatch sounds like a headline. It’s about a five-minute ride across town.
The hotel is a mid-range business property, the kind with a small lobby, a fitness center nobody uses, and a breakfast area that folds into a conference room. A staff member meets you at the entrance and apologizes twice for the elevator. Room 314. Ah yes, stairs it is. You grab your bag of tricks and box of life. You sherpa everything upstairs with your partner and find room 314 conveniently located at the opposite end of the hall. You knock, announcing your presence and get a one word Come….On…..In.
You find your patient Diane is sitting on the edge of the bed, fully dressed with a blazer still on, laptop open on the desk next to her, overnight bag half unpacked in the corner. She’s been at a two-day regional conference and clearly had no intention of calling 911 until she couldn’t talk herself out of it anymore. She looks scared in that quiet, controlled way, the way professionals get when something is happening to their body that they cannot explain and cannot fix with willpower. You can see the anxious jitters.

You introduce yourself and ask if it is ok if you partner gets her vitals. She replies. Yes……Please………
You pull a chair up and sit across from her while your partner starts getting the monitor ready.
You ask, “What’s going on?”
She replies……”I …got to my …..room after the……afternoon session……probably around four…..and I just couldn’t……catch my breath. I thought…..maybe I was dehydrated……or just tired. I laid down…. It didn’t help…..And then….. around five…… my chest started hurting…..
You ask, where in your chest does it hurt.
Diane points to the right side, says its……sharp. Worse when……..I take a deep breath.
You ask on a scale of one to ten what would you say it is?
She replies “Five…….maybe six now. It was……..a three at first.”
You ask if she has ever had a issue like this before.
She replies, “Never.”
You ask do you have any medical history I should know about? Heart, lungs, anything?”
She replies “No. I’m healthy….. I take a birth control pills…..vitamins……that’s all.”
You make a mental note. Oral contraceptive. You keep going.
You ask “Did you travel to get here?”
She replies “I drove……. from Cleveland……Nine hours Wednesday”
You reply with Wow, that’s a long way. Any stops along the way?
She replies “One gas……station. I wanted……..to make good time.”
Another mental note. Prolonged immobility. You continue, casually, letting her feel like it’s a conversation rather than a checklist.
You ask if any pain or swelling in your legs since the drive?”
She pauses. A noticeable pause.
“My right calf…….has been sore. I thought……it was from sitting……..in the car.”
You ask her to extend her leg. You compare both calves with your hands: the right is warmer, slightly larger, and tender to palpation along the medial aspect. You keep your face neutral.
You let her know, I am going to take a peak at your vitals and chat with my partner.
She asks “Do you think…….this is serious? Could……..it be a panic attack? I’ve……. had anxiety in the past.”
You let her know “It might be. The monitor will help us understand what’s happening. Let’s take a look together.”
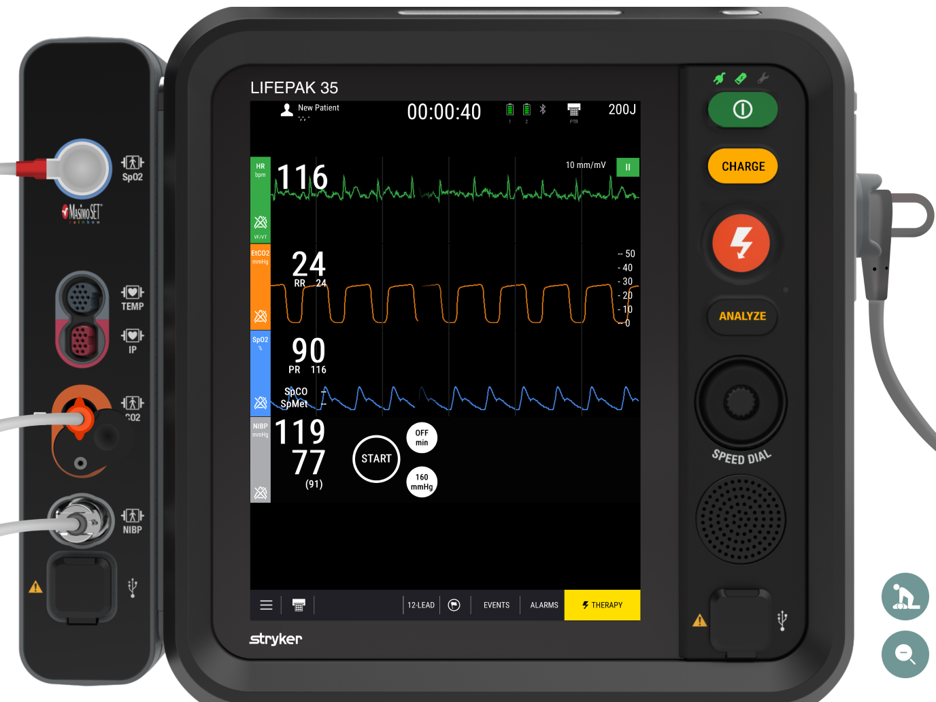
Your partner has the monitor running. You look at the screen. What do you think?
Normal waveform. Low EtCO2. High respiratory rate. Now think about what that combination means?
You also get crystal clear lung sounds.
You run the EKG. Sinus tachycardia. No STEMI. No obvious right heart strain pattern, though you know the EKG is neither sensitive nor specific for PE and won’t rule it in or out. The clinical picture assembles itself:
****Female on oral contraceptives. Eighteen hours of uninterrupted car immobilization. Unilateral calf pain and swelling. Sharp pleuritic right-sided chest pain. Tachycardia. Hypoxia. And a low EtCO2 with a normal waveform morphology.****
You look at Diane.
Hey Diane, I want to explain what my partner and I are thinking. Your breathing mechanics look really good, your lungs are moving air properly. But we’re seeing a situation where the oxygen and CO2 exchange in part of your lung isn’t working the way it should, and one of the reasons that happens is when a blood clot travels from the leg and blocks blood flow to part of the lung. Do you understand what I mean?”
She replies with “A pulmonary embolism?”
You reply “That’s what we’re concerned about, yes. We can’t confirm it in the field, that takes a CT scan but your history, your leg, and your vitals are all pointing in that direction. I want to get you to the hospital tonight so we can get that scan.”
She absorbs this. You can see her processor running.
She replies with “Is it… is this dangerous?”
You reassure her “It can be, which is why we want to move quickly. The good news is you called, you’re alert and talking to me, and we caught this. We’re going to take great care of you.”
She nods once, then looks at her laptop.
She asks “Can I just close that? I had a presentation I didn’t finish.”
You reply definitely Of course. Do you want to bring it with you?
She closes the laptop and stows it away.
You establish two IVs en route. You support her oxygen with 4 lpm. You call ahead to the receiving ED with a clear and detailed report: the history, the risk factors, the calf findings, the capnography pattern, the vitals. You use the word “concerned” because that is accurate and that is enough.
In the ED bay, as you help Diane onto the stretcher, she reaches over and touches your arm.
She ask “Can I…..ask you…..something?”
You reply with of course!
She asks “Was….I right to…..call?”
You reassure her that she absolutely was. You made exactly the right call, exactly when you needed to.”
She nods slowly. The CT techs are already heading her way.
Physiology Review: Dead Space (not that kind of dead): The Physiology of the Disconnect
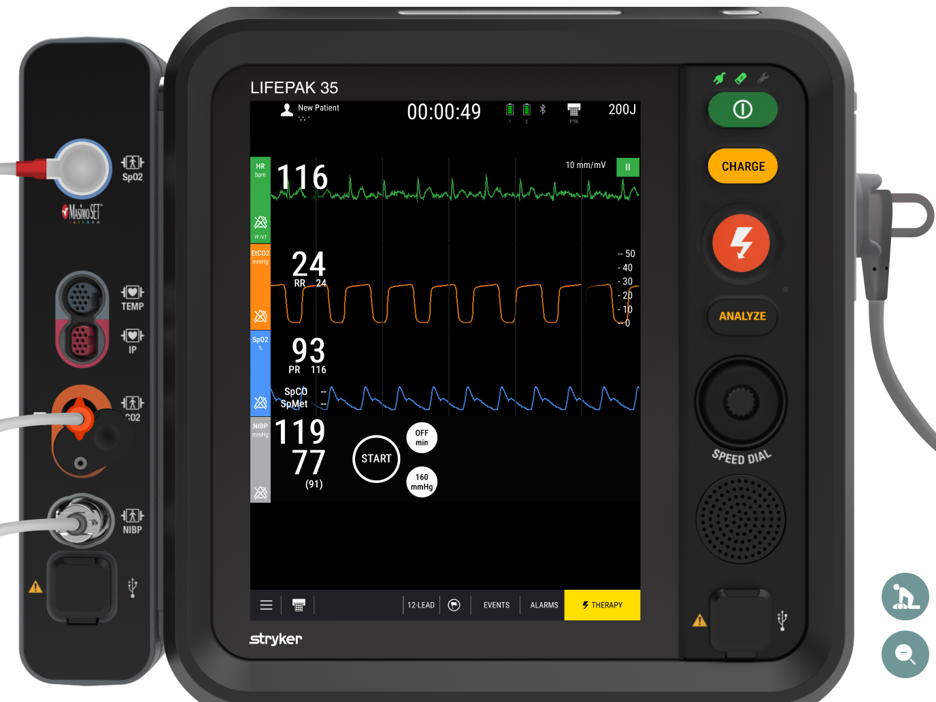
Diane’s waveform shape is clean and normal, she has a good Phase I, crisp upstroke, flat plateau (D > C), sharp downstroke. There is no shark-fin, no obstruction, no evidence of bronchospasm or obstructive disease. The mechanics of each breath are intact. But the value is 24 mmHg, and she’s breathing 24 times per minute. She is not hypoventilating. She is working hard to breathe. So why is the CO2 so low?
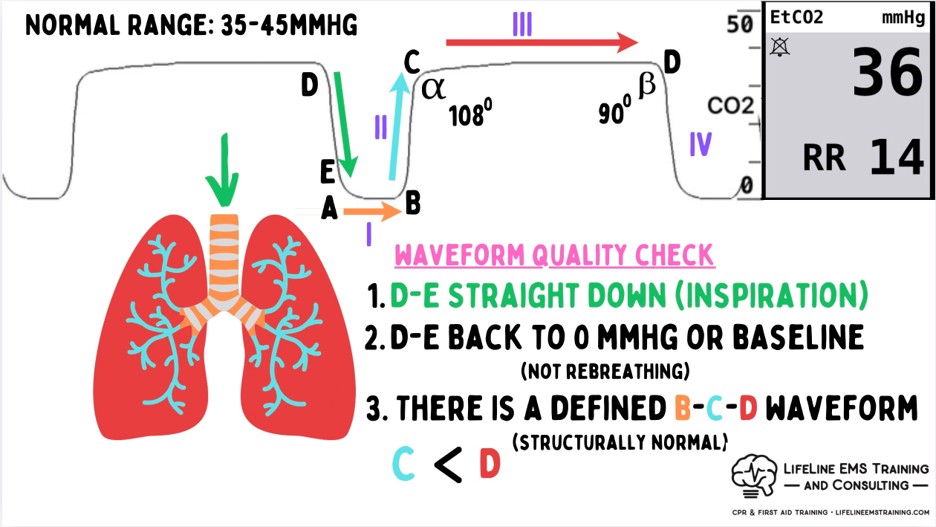
This is the physiology of dead space ventilation, and it is one of the most clinically important capnography concepts in emergency medicine.
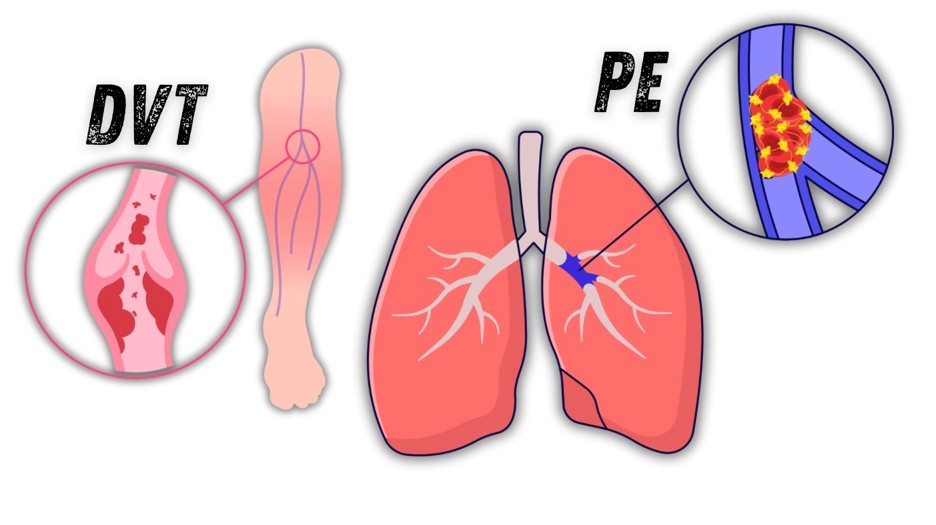
Under normal conditions, every alveolus that is ventilated is also perfused, CO2 from the blood crosses into the alveolus and is exhaled. In pulmonary embolism, a clot lodges in a pulmonary artery and eliminates blood flow to a section of lung.
Those alveoli continue to ventilate, they open and close with each breath but there is no perfusion. No blood is delivering CO2. So the air moving in and out of those alveoli contributes nothing to the exhaled CO2 reading. The result is a disproportionately low EtCO2 despite normal breathing mechanics and an appropriately high respiratory rate.
Diane is breathing twenty-four times per minute and getting an EtCO2 of 24. At rest, a healthy 44-year-old should have an EtCO2 of 35–45. She’s breathing nearly twice her normal rate and producing less than two-thirds of a normal CO2 value. The effort is not translating into output. The blood isn’t getting to the lung to make the exchange.
The waveform retains its normal morphology because the airways and functioning alveoli are structurally intact, the obstruction is vascular, not mechanical. This creates a specific and teachable pattern: normal waveform plus disproportionately low EtCO2 plus tachypnea plus hypoxia plus clinical risk factors should elevate pulmonary embolism on your differential immediately.
2Tachy/2Hypo- Tachycardia/Tachypnea, Hypocapnea/Hypoxia
The other issue PE patients experience is because they aren’t ventilating their CO2, they are retaining it. By retaining it they get a elevated PaCO2 and that creates vasodilation. So they get into a viscous cycle of dilated vessels, hypoxia, increased heart rate trying to compensate and an inability to bring in and bind O2 to the RBCs and out to the tissue. The retained CO2 plays into why their BP drops. They are a true ventilatory/perfusion mismatch!
In the prehospital setting, you can’t confirm this diagnosis, that requires imaging and/or lab work like a D-Dimer and a CT-A. But you can recognize the pattern, move with appropriate urgency, establish IV access, support oxygenation, and give the receiving team a clear, well-organized picture of why you’re concerned. That handoff changes the speed of the workup.
****Street Trick: Normal waveform plus low EtCO2 plus tachypnea plus a history that fits: think dead space, think PE. The airways are working. The blood isn’t getting there. That is what “disconnected” looks like on capnography. When the value and the waveform don’t match the effort, when someone is breathing hard and still not producing CO2, the story is in the vasculature, not the airway.****

Chris Kroboth has been a career paramedic/firefighter for over 17 years and in EMS for over 23. He has been in prehospital and in-hospital education for the past 18 years. His last assignment before returning to operations was as the EMS training captain in charge of continuing education programs and certification. He is also affiliate faculty with the Virginia Commonwealth University Paramedic Program. He is the U.S. clinical education manager for iSimulate and also facilitates national conference clinical challenges to include EMS World, ENA and NTI.
